
ITL-70c2ede76057
Juan Li, MD · Updated November 17, 2026
Watch the video

Key points
- Defer if you can. After an acute coronary syndrome, guidelines recommend revascularization as appropriate and deferral of elective noncardiac surgery, because the risk is greater than with chronic coronary disease.[1]
- The first weeks are the most dangerous. Stent thrombosis risk peaks in the first 4 to 6 weeks, and surgery within 1 month of a drug-eluting stent carried a 13-fold higher risk of cardiac death.[1]
- Wait about a year after a stent for ACS. Elective surgery should be delayed 12 months or more after a drug-eluting stent placed for an acute coronary syndrome.[1], [2]
- Keep aspirin. If dual antiplatelet therapy must be interrupted, aspirin should be continued whenever possible.[1]
- Plan combined therapy ahead. Clopidogrel is preferred when anticoagulants are added, DOACs are stopped 24 to 48 hours before surgery, and bridging is not recommended.[3], [4]
A patient had a non-ST-elevation myocardial infarction treated with a drug-eluting stent 6 weeks ago and now needs elective hip replacement. Should surgery wait, and what should happen to the antiplatelet drugs?[1], [2]
Why a recent ACS changes the risk
The 2024 AHA/ACC perioperative guideline states that a history of an acute coronary syndrome confers greater perioperative risk than chronic coronary disease and recommends revascularization as appropriate and deferral of surgery when possible. Patients whose PCI was performed for myocardial infarction have nearly 3-fold higher risks, perioperative stent thrombosis is greatest in the first 4 to 6 weeks, and in a cited Danish registry surgery within 1 month of a drug-eluting stent carried a 13-fold higher risk of cardiac death.[1]
Egholm and colleagues found that surgery within 12 months of a drug-eluting stent increased myocardial infarction (1.6% vs 0.2%, odds ratio 4.82) and concluded that surgery should be delayed at least 1 month; European guidance at the time recommended 12 months after a stent for an acute coronary syndrome.[2]

Figure 1. When to operate. Synthesized from the AHA/ACC guideline and Egholm et al.[1], [2] View larger.

How long to wait
The guideline advises delaying elective surgery 12 months or more after a drug-eluting stent placed for an acute coronary syndrome and at least 14 days after balloon angioplasty; if dual antiplatelet therapy must be interrupted, aspirin should be continued whenever possible.[1] Mortality after an acute coronary syndrome is highest in the 30 days after discharge; routine P2Y12 pretreatment in NSTEMI is not helpful, and data support early de-escalation of P2Y12 inhibitor intensity.[3]
When an anticoagulant is also needed
Bolliger and colleagues advise managing patients with a recent acute coronary syndrome or stent who also need anticoagulation like patients with atrial fibrillation undergoing PCI, preferring clopidogrel over more potent P2Y12 inhibitors. Procedures should be delayed until antiplatelet therapy can be stopped or reduced to aspirin; DOACs are stopped 24 to 48 hours before minor and major surgery, and bridging is not recommended.[4]
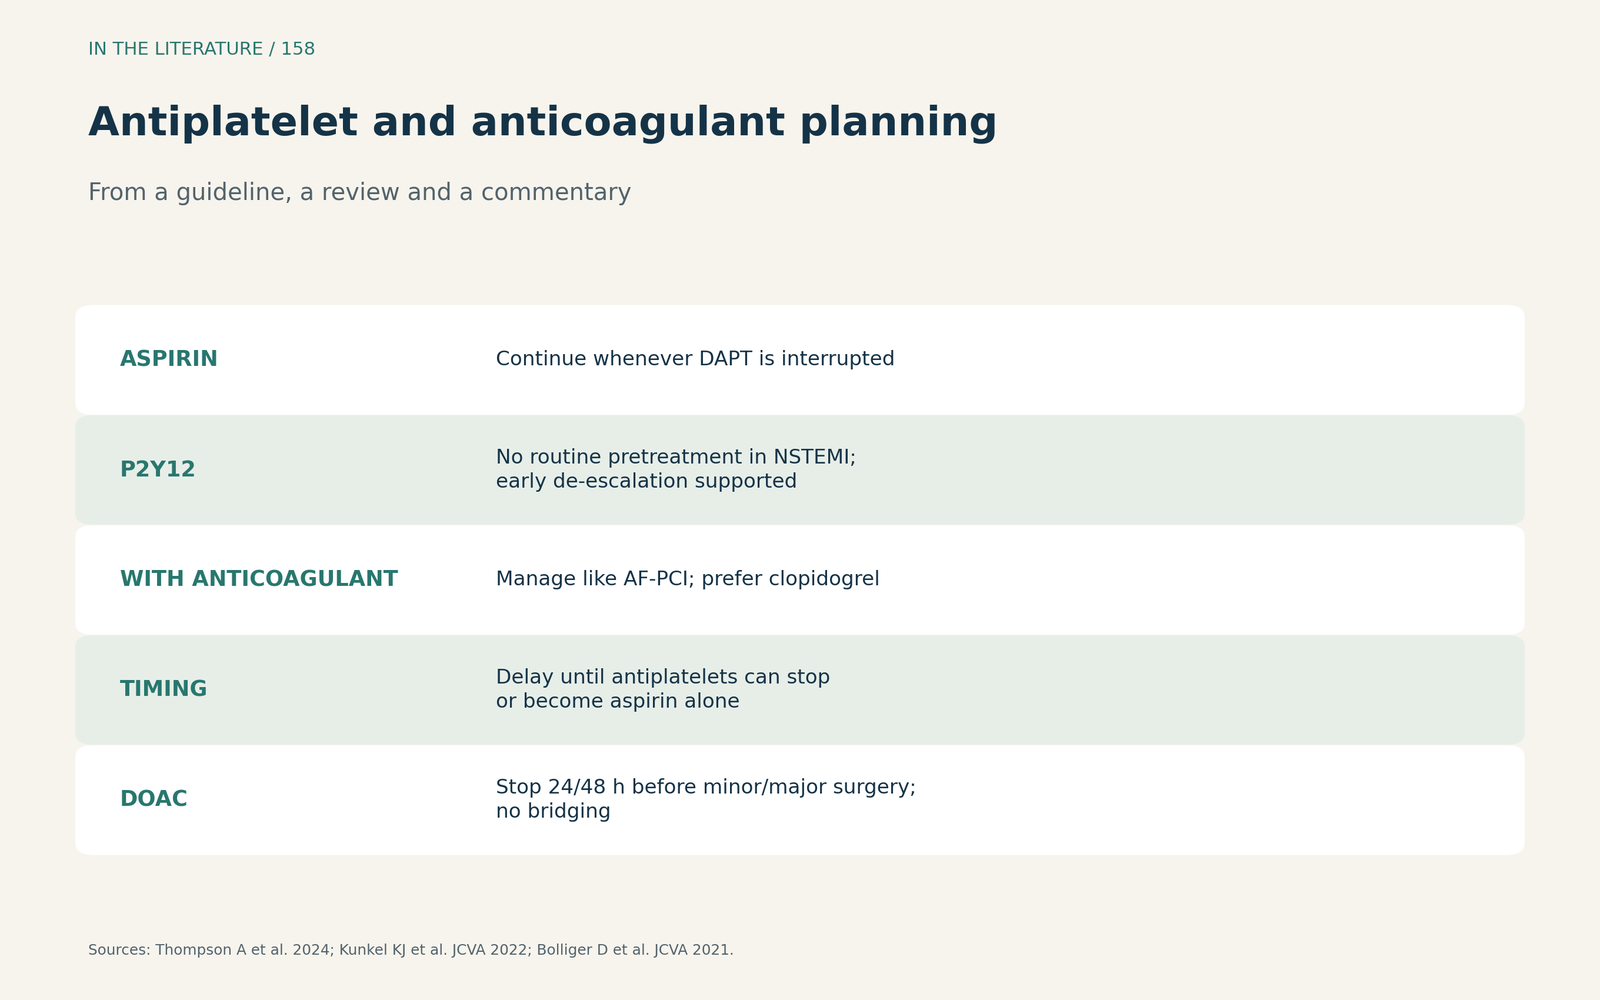
Figure 2. Antiplatelet and anticoagulant planning. Synthesized from the AHA/ACC guideline, Kunkel et al. and Bolliger et al.[1], [3], [4] View larger.

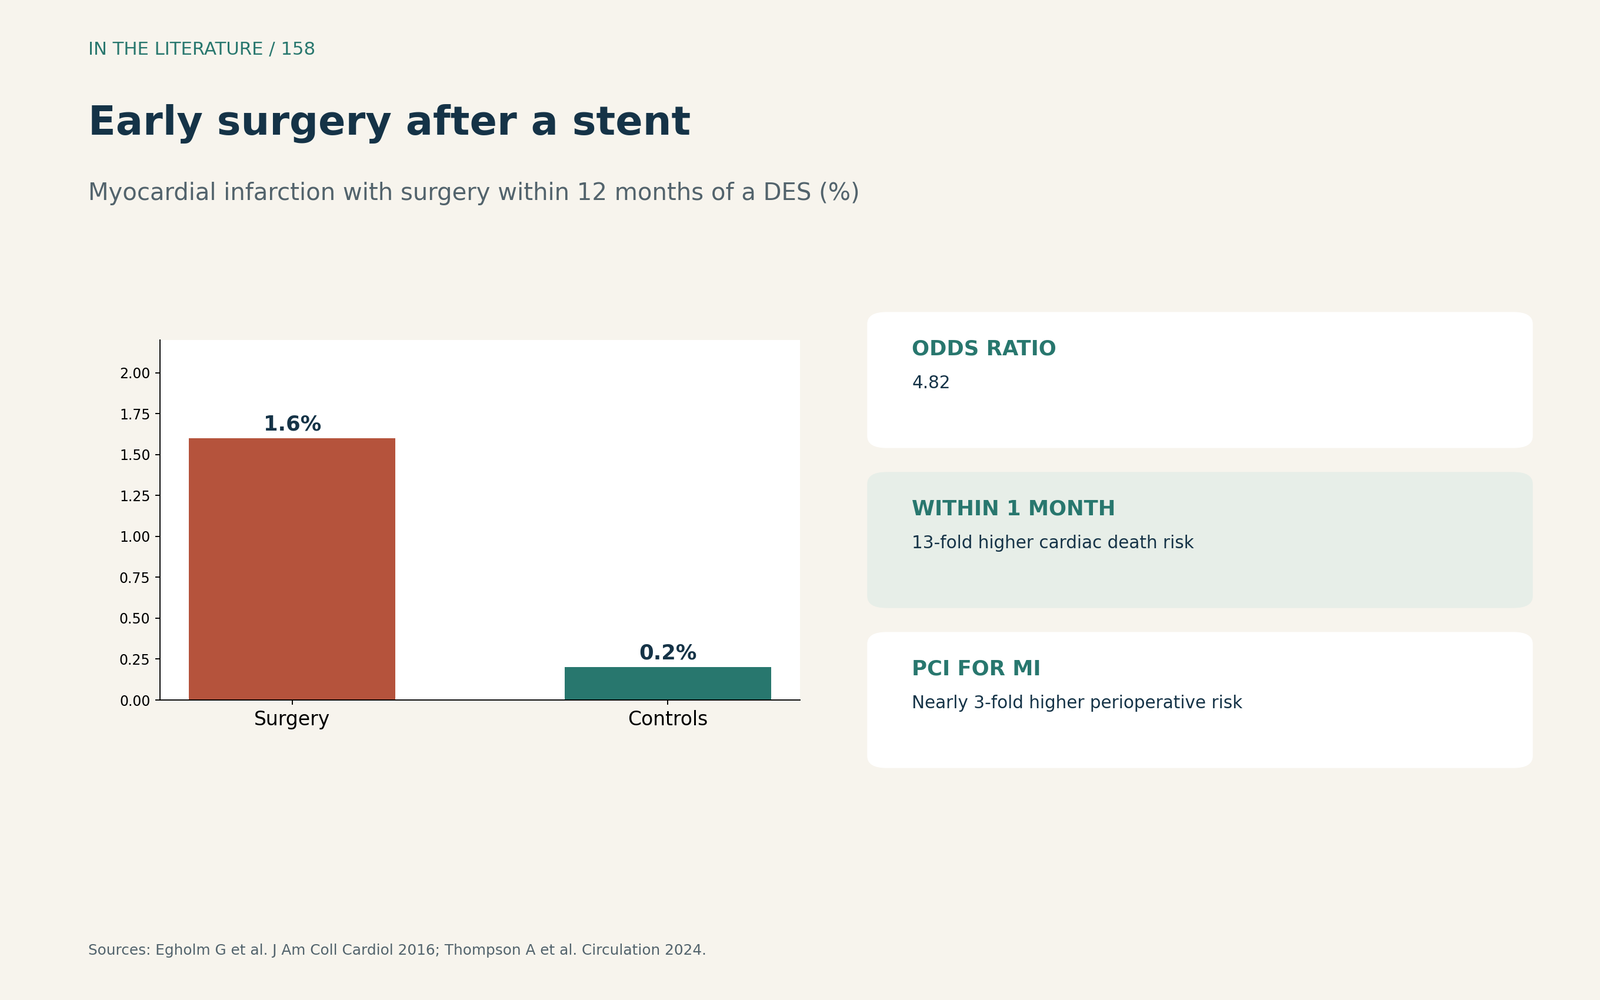
Figure 3. Early surgery after a stent. Redrawn from Egholm et al. and the AHA/ACC guideline.[2], [1] View larger.

Three takeaways
- Defer elective surgery after ACS. Revascularize as appropriate, and avoid the first weeks after a stent.[1]
- About 12 months after a stent for ACS. If surgery cannot wait, continue aspirin whenever possible.[1], [2]
- Plan antithrombotics together. Clopidogrel with anticoagulants, no bridging of DOACs.[3], [4]
References
- Thompson A, Fleischmann KE, Smilowitz NR, et al. 2024 AHA/ACC/ACS/ASNC/HRS/SCA/SCCT/SCMR/SVM guideline for perioperative cardiovascular management for noncardiac surgery: a report of the American College of Cardiology/American Heart Association Joint Committee on Clinical Practice Guidelines. Circulation. 2024;150(19):e351–e442. doi:10.1161/CIR.0000000000001285
- Egholm G, Kristensen SD, Thim T, et al. Risk associated with surgery within 12 months after coronary drug-eluting stent implantation. J Am Coll Cardiol. 2016;68(24):2622–2632. doi:10.1016/j.jacc.2016.09.967
- Kunkel KJ, Lemor A, Mahmood S, Villablanca P, Ramakrishna H. 2021 update for the diagnosis and management of acute coronary syndromes for the perioperative clinician. J Cardiothorac Vasc Anesth. 2022;36(8):2767–2779. doi:10.1053/j.jvca.2021.07.032
- Bolliger D, Fassl J, Erdoes G. How to manage the perioperative patient on combined anticoagulant and antiplatelet therapy: comments on the 2020 ACC consensus decision pathway. J Cardiothorac Vasc Anesth. 2021;35(6):1561–1564. doi:10.1053/j.jvca.2021.01.042