On 24 September 2024, ACC/AHA and seven collaborating organizations replaced one-time cardiac clearance with a proceed-or-pause pathway spanning selective testing, medication transitions, intraoperative judgment, and postoperative follow-up.
Reading Library · Anesthesia Epochs · 中文版
Watch the companion film
2024: AHA/ACC Perioperative Cardiovascular Guideline — Beyond Clearance · Watch on YouTube
Historical anchor: 2024. Date details and source qualifications are explained below.
“Cardiac clearance” is a remarkably durable phrase for something that does not exist.
It suggests a transaction: a patient is sent for an opinion, a specialist stamps the chart, and cardiovascular risk is left outside the operating room. The operation may now proceed because someone has declared the heart safe.
The perioperative cardiovascular guideline published online on 24 September 2024 starts from a different object. Its first take-home message is not clearance. It is a stepwise process for deciding when surgery should proceed and when the team should pause for more evaluation.
That shift from a noun to a verb is the historical center of the document.
The guideline's full name is nearly an organizational chart: AHA, ACC, ACS, ASNC, HRS, SCA, SCCT, SCMR, and SVM. ACC and AHA were joined by seven collaborating and endorsing organizations, making nine in all. A common shorthand calls it a ten-society guideline, but the source does not. Nor does the paper contain ten top messages. It contains nine.
The correction matters because this was not a document built to supply a memorable round number. It was built to make conditional decisions traceable.
The wrong object was a certificate
The 2024 guideline applies to adults undergoing noncardiac surgery and runs from preoperative evaluation through intraoperative management and postoperative follow-up. It explicitly supersedes the ACC/AHA guideline published in 2014.
Its pathway begins with time. Emergency surgery generally needs to occur in less than two hours. Urgent surgery allows at least two but fewer than twenty-four hours. A time-sensitive procedure may be delayed for as long as three months. An elective operation can wait for a complete evaluation.
These categories prevent a chronic cardiovascular question from acquiring the same practical meaning in every setting. A test that can reasonably be obtained before an elective operation may be a dangerous delay before an emergency one.
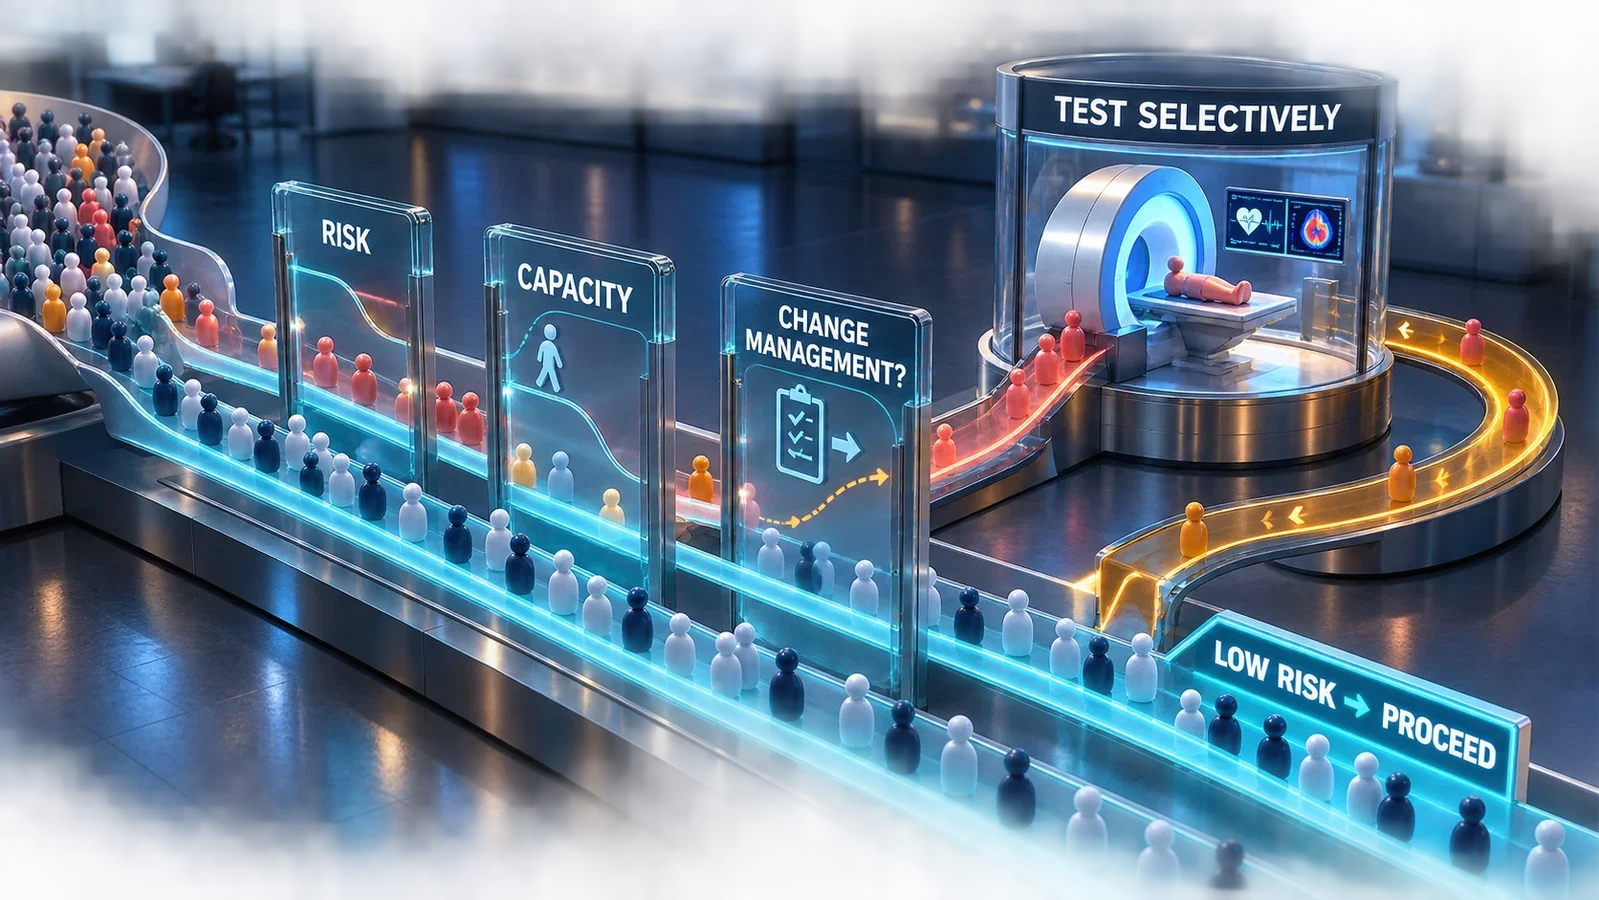
Risk is another gate, not a verdict. The document generally describes predicted major adverse cardiovascular-event risk below 1% as low and 1% or greater as elevated, while acknowledging that calculators, populations, and endpoint definitions differ. Functional capacity adds another dimension. Less than 4 metabolic equivalents or a Duke Activity Status Index score of 34 or lower counts as poor capacity.
But poor capacity is not a hidden order for a stress test. It is one input among several: the risk of the operation, the patient's clinical risk, and whether a test result would change a decision that matters.
The useful question is no longer, “Has this patient been cleared?” It is, “Where is the patient on the pathway, and is there a reason to stop here?”
Surgery does not create a new indication for testing
The second take-home message supplies the intellectual brake. Cardiovascular screening and treatment before noncardiac surgery should follow the same indications used for nonsurgical patients. They should also be timed to avoid delaying surgery, overscreening, and overtreatment.
A date on an operating-room schedule therefore cannot transform an otherwise unnecessary test into an essential one.
Stress testing makes the principle concrete. It may be considered for a selected patient facing elevated-risk surgery who also has poor or unknown functional capacity and elevated predicted cardiovascular risk. Even then, the result should have a plausible route to changing management. Routine testing offers no benefit for patients at low perioperative risk, those with adequate capacity and stable symptoms, or those having low-risk procedures.
The same logic constrains coronary CT angiography, invasive angiography, and revascularization. They are not decorations for a more impressive clearance packet. The guideline repeatedly returns to indications that would apply independently of the proposed operation.
This is not minimalism for its own sake. Every test opens a branch: an equivocal result, another image, an invasive procedure, a treatment delay, or a therapy whose harms may outweigh its value. A stepwise pathway asks whether information can improve the decision before it asks how to obtain more of it.
The pathway does not end at induction
The official Guideline-at-a-Glance selected four areas to illustrate changes from 2014: stress testing, sodium-glucose cotransporter-2 inhibitors, myocardial injury after noncardiac surgery, and atrial fibrillation.
Together they show why “preoperative evaluation” became too small a frame.
SGLT2 inhibitors bring long-term treatment of diabetes, heart failure, and obesity into the surgical clock. The 2024 document recommends interrupting these agents three to four days before scheduled surgery to reduce the risk of perioperative metabolic acidosis. In a history article, the important fact is not a patient-specific medication instruction. It is that a rapidly expanding chronic therapy created a new perioperative transition to manage.
MINS pulls attention in the opposite direction, beyond the procedure. Myocardial injury may be clinically silent when anesthesia, analgesia, and surgical pain obscure ischemic symptoms. The guideline says postoperative troponin measurement may be reasonable at 24 and 48 hours in selected elevated-risk groups. It also states that routine screening after low-risk surgery, without symptoms or signs of myocardial ischemia or infarction, provides no benefit.
The supportive text cites cohorts in which MINS occurred in roughly 20% of noncardiac surgical patients and was associated with about 10% mortality at thirty days. Those are approximate estimates from particular study populations, not permanent constants for every hospital or patient. The document is equally explicit about the unresolved half of the story: the best management strategy after surveillance identifies MINS remains uncertain.
New atrial fibrillation lengthens the pathway again. The immediate task is to look for reversible contributors such as sepsis, anemia, or pain. A decision about postoperative anticoagulation must balance thromboembolic risk against perioperative bleeding. Follow-up is recommended for stroke-risk assessment and AF surveillance because an arrhythmia first recognized around surgery may recur after the admission has ended.
Two other messages resist automatic care. Bridging an interrupted oral anticoagulant should be reserved for patients at the highest thrombotic risk, not used routinely in the majority. Focused cardiac ultrasound may help evaluate otherwise unexplained hemodynamic instability in an emergency when appropriate expertise is present, but it must not be promoted into a replacement for comprehensive transthoracic echocardiography.
Medication transitions, selective surveillance, arrhythmia follow-up, anticoagulant interruption, and bedside imaging become parts of one temporal system. The guideline reaches across the operating room rather than stopping at its door.
A recommendation can be strong while the map remains incomplete
ACC/AHA guidelines use two axes that are easy to collapse in casual retelling. Class of Recommendation expresses the benefit-risk judgment and the strength of the action. Level of Evidence describes the type and quality of evidence supporting it. They are related, but they are not interchangeable.
The official online data supplement makes the mixed foundation unusually visible. Its workbook contains 358 evidence-table records. One sheet holds 115 records classified as randomized trials or meta-analyses including randomized trials. Another holds 243 nonrandomized records. The rows are not necessarily 358 unique studies; the same publication can appear more than once when it informs different questions.
Even with that qualification, the architecture is revealing. Nonrandomized records outnumber randomized or meta-randomized records by more than two to one. Cohort studies dominate the nonrandomized sheet, alongside registries, descriptive designs, case series, and other forms of evidence.
This is not an accusation that the guideline is “not evidence based.” It is a more accurate account of what evidence-based perioperative medicine often has to do. Questions about rare harms, emergency timing, complex anatomy, drug interruption, and system organization cannot all be answered by large randomized trials. A committee must distinguish what is known, what can reasonably be recommended, and where confidence remains limited.
The final evidence-gap section refuses to disguise those limits. Few multidisciplinary care-delivery models have been rigorously studied for their effects on testing or cardiovascular outcomes. No perioperative risk index has been established as the preferred one. There are no perioperative randomized trials of rate versus rhythm control for new-onset AF in noncardiac surgery. Evidence for preoperative revascularization in stable patients is limited. Questions remain about blood-pressure targets, recent stroke, several medication strategies, imaging and circulatory-support devices, pulmonary-artery catheters, and optimal MINS therapy.
The guideline is useful partly because it marks those blank spaces instead of coloring them in.
One deleted row shows why the medium is not the master
The publication acquired a formal correction.
One change fixed the expansion of ASH in a table legend: American Society of Hypertension, not American Society of Hematology. The other deleted an entry in the moderate-thrombotic-risk mechanical-valve column of Table 14: a mitral valve without major stroke risk factors.
The full guideline incorporates both corrections. The official 110-slide teaching deck does not. Its slide 83 still contains the deleted valve entry.
That discrepancy does not invalidate the guideline, and the correction did not remake the entire pathway. It does establish a practical hierarchy. A slide deck is a dissemination instrument. Once it conflicts with corrected master text, it cannot remain the clinical authority simply because it is easier to read.
Version control is not clerical trivia when a table can shape anticoagulant management. It is part of safety.
Publication is not implementation
The 2024 event was not that nine organizations invented stress testing, troponin surveillance, SGLT2 interruption, AF follow-up, or focused ultrasound. Each component had its own prior history.
What changed was their arrangement. Risk assessment determines whether to proceed or pause. Testing must be capable of changing care. Chronic therapies enter a perioperative time line. Intraoperative instability can prompt focused evaluation. Postoperative myocardial injury and arrhythmia remain visible after the operation appears to be over.
Yet a published pathway is not evidence that hospitals adopted it, and a recommendation is not evidence that outcomes subsequently improved. The preamble says that guidelines describe practices suitable for most, not all, circumstances and should not replace clinical judgment. It also says recommendations become effective only when clinicians and patients follow them, supported by shared decision-making.
That is the last boundary the historical account must preserve.
“Cardiac clearance” asks for a stamp. The 2024 guideline asks a sequence of harder questions. What is the risk now? Which information would change management? Is delay justified? What must be managed through the operation? What injury or arrhythmia must still be followed afterward? Where does evidence end and judgment begin?
On 24 September 2024, nine organizations did not make perioperative cardiovascular risk disappear.
They replaced a certificate with a map.
Sources and reading limits
Sources: Thompson A et al. J Am Coll Cardiol. 2024;84(19):1869-1969. PMID 39320289. DOI 10.1016/j.jacc.2024.06.013; Circulation. 2024;150(19):e351-e442. PMID 39316661. DOI 10.1161/CIR.0000000000001285; Bhave NM et al. J Am Coll Cardiol. 2024;84:1970-1975. DOI 10.1016/j.jacc.2024.08.018; official online data supplement and slide set; JACC correction DOI 10.1016/j.jacc.2024.10.107; Circulation erratum PMID 39556658. This is a history of a corrected guideline and its evidence architecture, not individualized medical advice.
Visual interpretations
These illustrations explore the setting and ideas. Depicted people, actions, instruments and documents are reconstructions, not evidence of their exact historical appearance.


Continue exploring
Related reading connects shared questions and contexts; it does not by itself establish historical influence.
Related reading
- 2008: STOP-Bang Makes OSA Risk Visible Before the Operating Room
- 2010: Makary's Five-Item Study Brings Frailty into Preoperative Assessment
- 2015: Care for the Older Surgical Patient Becomes a Perioperative Pathway
- 2018: Prediction Enters the Monitor, Not the Treatment Order
- 2022: POISE-3 Finds Tranexamic Acid Cuts Bleeding Without Proven Cardiovascular Noninferiority
- 2024: ASA Revises PACU Handoff to 'Stay with the Patient'
The Source Room · About & Editorial Method
Sources and reading limits are stated above. Illustrations are labelled as original source images or AI-made. Historical accounts are educational; they are not current treatment instructions.